
INTRODUCTION
Staphylococcus aureus is a gram-positive, ubiquitous coccus, capable of remaining viable in the environment for a long time,(1) humans are the main reservoir of this microorganism, which can colonize the anterior portion of the nasopharynx and, frequently, the skin.(2,3,4) It can be carried asymptomatically in a large number of healthy people or symptomatically causing pathologies,(4) such as, for example, skin infections including simple folliculitis, impetigo, as well as boils and carbuncles, present in surgical wounds, which can be a focus for the development of systemic infections.(5)
Methicillin-resistant Staphylococcus aureus (MRSA) is a specific strain of S. aureus that is resistant to all antibiotics of the β-lactam class,(6,7) known as nosocomial pathogens of paramount importance throughout the world.(7) Latin America, in particular, should be highlighted due to the increase in multidrug-resistant strains acquired in its hospitals.(8,9) Its epidemiology is constantly changing, both in terms of circulating clones and their antimicrobial resistance profiles and these data vary depending on the region and country.(8,10,11) An important risk factor for transmission and subsequent infection by the pathogen is related to its presence in the nasal cavity.(12,13,14) Scientific evidence shows that healthcare professionals can act as vehicles for MRSA transmission.(7,15)
The main source of MRSA transmission within hospitals is the lack of hand hygiene, as this is the most important and efficient method of reducing the spread of microorganisms.(16) It is worth noting that before and after contact with the patient, hands, equipment and the environment must be correctly decontaminated. Personal protective equipment (PPE) such as gloves, aprons, and other equipment used by healthcare professionals in patient care, such as thermometers, sphygmomanometers, phonoendoscopes, and otoscopes, can be contaminated with MRSA.(17) Furthermore, it is important to highlight that patient rooms and the objects found in them can also act as reservoirs for the transmission of resistant agents.(8)
Among the main prophylactic measures for MRSA is the education of professionals and hand washing. Accurate and rapid detection of MRSA is essential, not only for the therapeutic choice of the most appropriate antimicrobial for each patient, but also for controlling the transmission of MRSA.(18)
Given the growth of bacterial resistance mechanisms in hospital and community strains and that the carriage of MRSA represents a significant risk factor for causing infections, this study aims to highlight the importance of MRSA research, to raise awareness among professionals and health academics about the care that should be taken in the hospital context and the community. As observed in several studies, the prevalence of nasal colonization by MRSA in patients receiving healthcare is frequent, however, this topic has been little explored in healthy individuals in the general community, and Brazilian scientific production on the subject is scarce.
METHODS
This is a cross-sectional study, in which the presence of MRSA was evaluated in the nasal cavities and hands of academics in the health field in the city of Juiz de Fora - MG. The study was performed by collecting samples using sterile, hand, and nasopharyngeal swabs from 60 students from a health college in Juiz de Fora - MG. The collection was performed during the months of March and April 2015.
After collecting the samples, they were identified and sent in Stuart medium to the microbiology laboratory of the educational institution, where they were inoculated in BHI medium (Mbiolog diagnósticos Ltda.) and incubated in an aerobiosis oven (Fanem 502) at 36ºC /- 1ºC for 24 hours.
After the incubation period, the reinjecion in BHI solution was performed in salted Mannitol Agar (RenyLab/ Química e Farmacêutica). The plates were incubated at 36ºC /- 1ºC for 24/48 hours. After incubation, the morphotinctorial characteristics of each colony were observed, and subsequently, biochemical identification tests were performed, such as catalase, coagulase, and DNAse. The strains identified as Staphylococcus aureus were subjected to antimicrobial sensitivity testing (TSA), using the Kirby-Bauer method, and the Cefoxitin resistant assay (30µg) was performed, in accordance with the CLSI standardization - Clinical Laboratory Standards Institute, 2015.
This study was previously approved by the institutional Research Ethics committee in accordance with resolution 466/12 of the National Health Council, under Opinion Number 1,021,243 and Reporting Date at 03/31/2015.
RESULTS
60 health academics from a college in Juiz de Fora participated in the research, 37 females and 23 males, aged between 18 and 30 years old. Of the participants, 30 had no contact with the hospital environment and 30 had contact with the hospital environment, at least 3 months before collection.
Two samples were collected from each student, one from the nasal cavities and one from the hands, totaling 120 samples. Among the samples collected, 25 (20.83%) tested positive for Staphylococcus aureus, 15 (12.5%) being positive in the nasal cavities and 10 (8.33%) on hands. The 25 samples positive for S. aureus were subjected to cefoxitin sensitivity testing, and eight strains of S. aureus were found to be resistant to cefoxitin, which characterizes the MRSA strain. Of the 25 positive samples, 15 (12.5%) belonged to women, with nine (7.5%) present in the nasal cavities and six (5%) present on the hands, and 10 (8.33%) samples belonged to men, with six (5%) present in the nasal cavities and four (3.33%) present on hands.
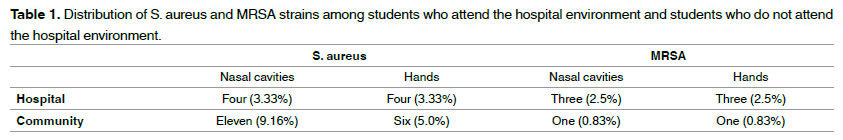
Of the positive results for MRSA, two (1.66%) samples were from academics who do not frequent the hospital environment, with one academic colonized on the hands and the other academic colonized in the nasal cavities. The other six (5.0%) samples were from academics who frequent the hospital environment, being samples from three academics, all colonized both on their hands and in their nasal cavities. Of the eight MRSA samples, five (4.16%) belonged to women, three (2.5%) were present in the nasal cavities and two (1.66%) were present on hands, and three (2.5%) samples belonged to men, with one (0.83%) present in the nasal cavity and two (1.66%) present on hands. According to Table 1.
Methicillin-resistant S. aureus (MRSA) are microorganisms responsible for well-known infections worldwide and have been highlighted due to their multi-resistance to the antimicrobials most used in therapy and characterized by their easy intra-hospital dissemination.(19,20) Contaminations traditionally caused by MRSA, which were previously limited to the hospital environment, may now be present in community-associated or community-acquired infections.(21)
The in vitro resistance profile to cefoxitin also expresses resistance to other drugs such as methicillin, oxacillin, penicillins, carbapenems, cephalosporins, piperacillin, tazobactam, and imipenem.(22) S. aureus resistance to antimicrobials occurs through the development of mutations in their genes or through resistance genes acquired from other bacteria. Resistance to methicillin is determined through a chromosomal gene of the bacteria – mecA - which leads to modifications in the beta-lactam receptor, stimulating the production of a penicillin-binding protein (PPB2a) with low affinity for the antibiotic.(23)
In this study, samples were collected from students’ hands and nasal cavities, and microbial growth was possible in all of them. In this way, an expected profile was observed, since these microorganisms are part of the normal microbiota and do not necessarily represent health risks.(24,25,26)
In this study, through the coagulase test, the presence of S. aureus was detected in 25 (20.83%) of the 120 samples collected, 15 (60%) of which were present in the nasal cavities and 10 (40%) on the hands. Of the 25 samples analyzed, 15 belonged to women, with nine present in the nasal cavities and six present on the hands and 10 samples belonged to men, six present in the nasal cavities and four present on hands. In a microbiological study performed by Ribeiro et al.,(27) in which they evaluated the presence of S. aureus and MRSA in university students, it was observed that among the 102 students evaluated, 39 (38.2%) presented S. aureus and 63 (61.8%) S. aureus coagulase negative (SCN). Of the students who presented S. aureus, 19 (48.7%) were colonized in the nasal cavities, 6 (15.4%) on hands and 14 (35.9%) in both. Of the 39 students with S. aureus, 24 were female and 15 were male.
According to what was observed among the 25 positive results obtained, the main site of colonization by S. aureus was the nasal cavities, totaling 15 (60%) samples, four from academics who have contact with the hospital environment, and 11 from academics who have no contact with the hospital environment, presenting a profile similar to the study by Ribeiro et al,(27) mentioned previously, which presents a greater profile of colonization by S. aureus in the nasal cavities followed by the hands. Therefore, we can state that the data found are in agreement with the literature studied, in which the nasal cavities constitute the main site of colonization of S. aureus.
Through TSA, the presence of MRSA could be observed in eight of the samples analyzed. Among the MRSA samples, four were found in the nasal cavities, three found in students who attend the hospital environment and one found in a student who does not attend the hospital environment. The other four positive results refer to hand samples, three of which were found in academics who attend the hospital environment and one found in an academic who does not attend the hospital environment. Of the eight MRSA samples, five belonged to women, with three present in the nasal cavities and two present on hands, and three samples belonged to men, one present in the nasal cavity and two present on hands. As observed in the study by Ribeiro et al.,(27) two of the 39 students colonized by S. aureus had MRSA strains, with one student carrying MRSA in the nose and the other student carrying the strain on hands.
It can then be stated that the results found in the present study are similar to those found by most authors who researched S. aureus and its resistance mechanisms. Given these results, it is indisputable that it is necessary to perform systematic awareness measures in academia and professionals regarding the importance of correct hand washing in controlling infections acquired in the community and hospitals.
CONCLUSION
The presence of MRSA was verified in eight (6.66%) of the 120 samples analyzed. Among the eight samples analyzed, it was found that 6 (75%) belonged to students who attend the hospital environment, demonstrating a higher prevalence when compared to students who do not attend the hospital environment (25%).
According to the results observed, it is concluded that resistance to cefoxitin is already evident in community samples of S. aureus and deserves attention when admitting patients to hospitals since they could become reservoirs of the bacteria and thus colonize the professionals who deal with such patients.
It is clear that it is essential to adopt more effective control measures in the case of MRSA strains. It is worth highlighting that the awareness of health professionals and academics is essential for the prevention of hospital infections, paying attention to all proposed measures, from hand washing to the rational use of antimicrobials. Given this, it is important to remember that such mobilization must also extend to the community environment, due to the change in the epidemiological pattern of MRSA strains.
REFERENCES
1. Kurashige, E.J.O.; Oie,S.; Furukawa, H. Contamination of environmental surfaces by methicillin-resistant Staphylococcus aureus (MRSA) in rooms of in patients with MRSA-positive body sites. Braz. J. Microbiol. 2016; 47:703-5.
2. Bannerman, T. L. Staphylococcus, Micrococcus, and other catalase-positive cocci that grow aerobically. Manual of Clinical MicroBiology 2003; 1:384-404.
3. Carvalho, C. E. et al. Monitoramento microbiológico sequencial da secreção traqueal em pacientes intubados internados em unidade de terapia intensiva pediátrica. J. Pediatr. 2005; 81:29-33.
4. Cavalcanti, S. M. M. et al. Prevalence of Staphylococcus aureus introduced into intensive care units of a university hospital. The Braz. j. infect. dis. 2005; 51:56-63.
5. Ratti, R. P.; Sousa, C.P. Staphylococcus aureus meticilina resistente (MRSA) e infecções nosocomiais. Rev. ciênc. farm. básica apl. 2009; 30:9-16.
6. Gunawardena, N. D. et al. Molecular identification of methicillin resistance and virulence marker in Staphylococcus aureus. Sri Lanka Journal of Infectious Diseases 2012; 2:18-29.
7. Mahalingam, U.; Thirunavukarasu, K.; Murugananthan, K. Methicillin resistant Staphylococcus aureus among nurses in a tertiary care hospital in northern Sri Lanka. Ceylon Med J 2014; 59:63-5.
8. Alvarez, C.; Labarca, J.; Salles, M. Prevention strategies for methicillin-resistant Staphylococcus aureus (MRSA) in Latin America. Braz. j. infect. Dis 2010; 14:107-18.
9. Kakhandki, L. S.; Peerapur, B. V. Study of nasal carriage of MRSA among the clinical staff and health care workers of a teaching hospital of Karnataka, India. Al Ameen Journal of Medical Sciences 2012; 5:367-70.
10. Barber, M. Methicillin-resistant staphylococci. J Clin Pathol 1961; 14:385-93.
11. Chabbert, Y. A. ; Baudens, J. G. Souches de staphylocoques resistants naturellement a la meticilline et a la 5 methyl-3-phenyl-4-iso-oxazyl penicilline (P12). Ann. Inst. 1962; 103:222-30.
12. Kluytmans, J.; Belkum, A.; Verbrugh, H. Nasal carriage of Staphylococcus aureus: epidemiology, underlying mechanisms, and associated risks. Clin Microbiol Rev 1997; 10:505-20.
13. Wertheim, H. F. et al. The role of nasal carriage in Staphylococcus aureusinfections. Lancet Infect Dis 2005; 5:751-762.
14. Prates, K.A. et al. Nasal carriage of methicillin-resistant Staphylococcus aureus in university students. Braz. j. infect. dis 2010; 14:316-18.
15. Gould, F. K. et al. Guidelines (2008) for the prophylaxis and treatment of methicillin-resistant Staphylococcus aureus (MRSA) infections in the United Kingdom. J Antimicrob Chemother 2009; 63:849-61.
16. Aguilera, S. L. et al. Colonización nasal por Staphylococcus aureus en estudiantes de medicina: importancia en la transmisión hospitalaria. Enferm. infecc. microbiol. clín. 2013; 31:500-5.
17. Singh, D. et al. Bacterial contamination of hospital pagers. Infection Control & Hospital Epidemiology 2002; 23:274-276.
18. Malini, J. et al. Methicillin-resistant Staphylococcus aureus carriage among the health care workers in a tertiary care hospital. J Clin Diagn Res 2012: 6:791-3.
19. Menegotto, F. R.; Picoli, S. U. Staphylococcus aureus oxacilina resistente (MRSA): incidência de cepas adquiridas na comunidade (CA-MRSA) e importância da pesquisa e descolonização em hospital. Rev. bras. anal. clin. 2007; 39:147-50.
20. Sales, L. M.; Silva, T. M. Staphylococcus aureus meticilina resistente: um desafio para a saúde pública. Acta Biomedica Brasiliensia 2012; 3:1-13.
21. Gelatti, L. C. et al. Staphylococcus aureus resistentes à meticilina: disseminação emergente na comunidade. An. Bras. Dermatol. 2009; 84:501-6.
22. Ferreira, W. A. et al. Prevalência de Staphylococcus aureus meticilina resistente (MRSA) em pacientes atendidos em ambulatório de dermatologia geral em Manaus - Amazonas. Rev. patol. Trop. 2009; 38:83-92.
23. Santos, A. L. et al. Staphylococcus aureus: visitando uma cepa de importância hospitalar. J. Bras. Patol. Med. Lab. 2007; 43:413-23.
24. Pereira, P.M.A. Et al. Resistência aos antimicrobianos em estafilococos coagulase-negativa isolados em hemocultura. J. bras. med. 2007; 93:13-6.
25. Souza Junior, F. C. et al. Prevalência de Staphylococcus spp resistentes à meticilina isolados em uma maternidade escola da cidade de Natal, Estado do Rio Grande do Norte. Rev. Soc. Bras. Med. Trop. 2009; 42:179-82.
26. Moraes, C. L.; Ribeiro, N. F. G.; Costa D. M. Contaminação de equipamentos e superfícies de unidades de terapia intensiva de uma maternidade pública por Staphylococcus coagulase negativa. Rev. patol. Trop. 2013; 42:387-94.
27. Ribeiro, I. F. et al. Identificação de Staphylococcus aureus e Staphylococcus aureus resistente à meticilina em estudantes universitários. Rev. ciênc. farm. básica apl 2014; 35:301-4.